Download the guide & starting assumptions · Explore the regional capacity ↓
Start with the full possibility
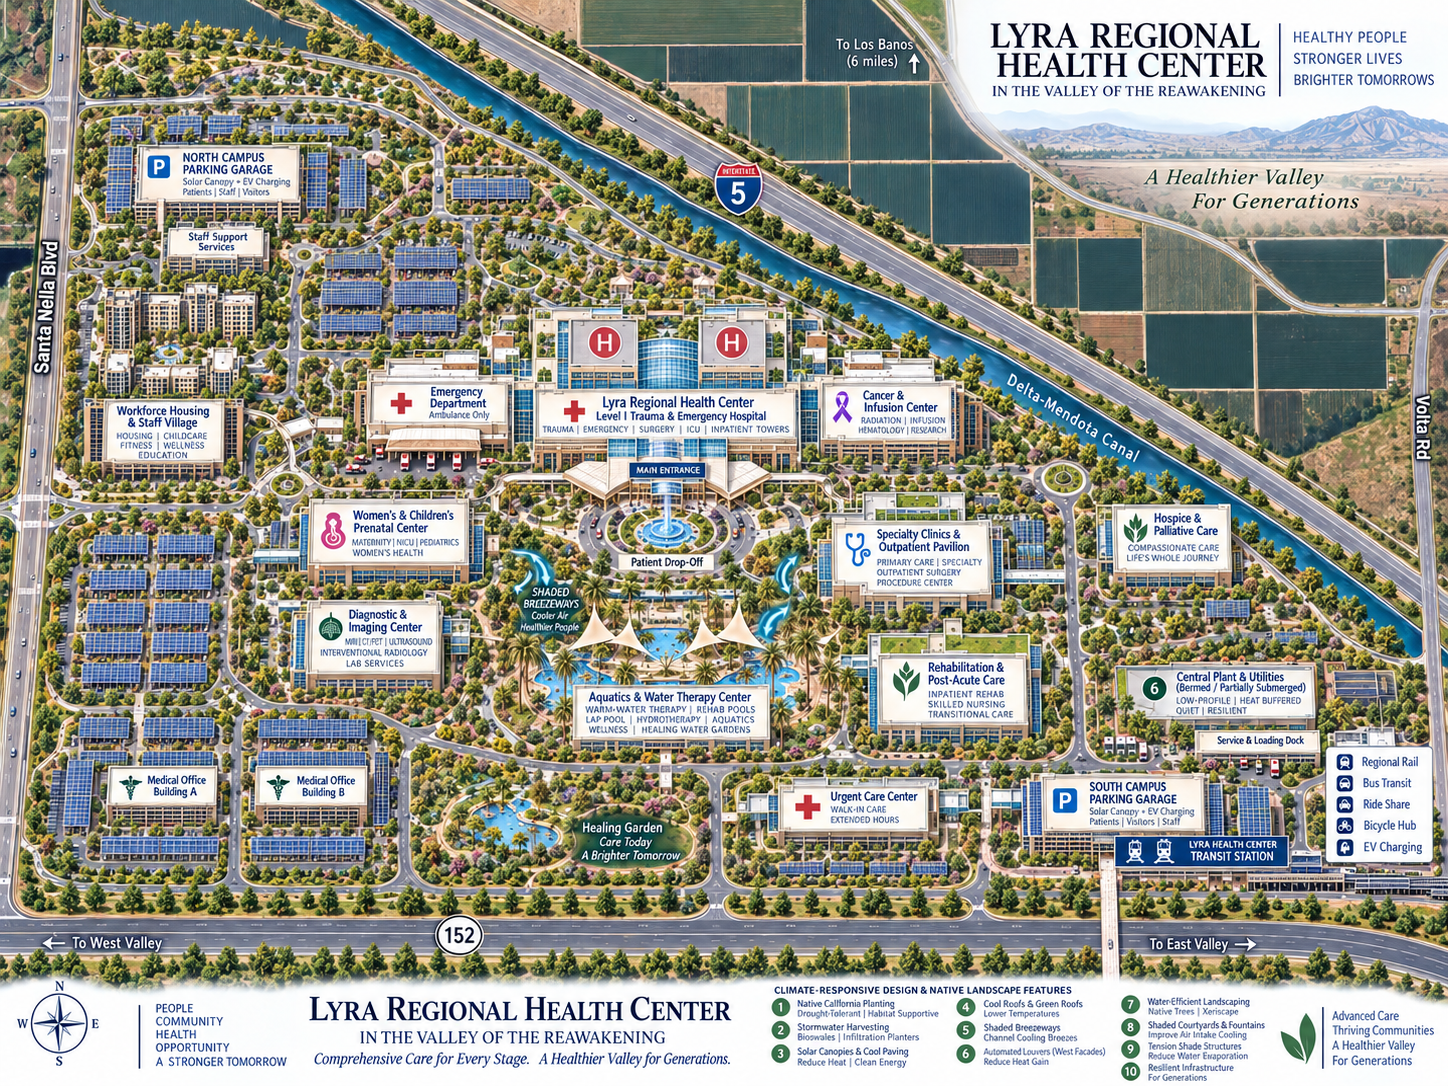
The Lyra Regional Health Center vision is a roughly 200-acre health district near Santa Nella: a major hospital growing to 600–700 beds, 300–500 workforce apartments / homes, advanced neurological and other high-acuity care, patient and family lodging, teaching, research, childcare and rehabilitation. Its regional referral ambition reaches approximately 100–200 miles around the hospital.
The proposed Stanford–Kaiser partnership would combine academic specialty and hospital care with integrated community care and prevention. Local hospitals and clinicians would help form a regional network serving people across insurance arrangements. The aim is meaningful additional clinical capacity for the Valley and California, with homes and training that support the people delivering it.
This guide explores what could be possible. Its physical scope, budgets, savings and partner roles are assumptions for discussion. No participation, parcel, award or operating forecast is confirmed. The point is to make the idea concrete enough for residents, potential partners and Merced County to improve it.
A regional referral center reaching 100–200 miles
The ambition is a major center for the western San Joaquin Valley with a specialty-referral network reaching roughly 100–200 miles around the hospital. This is the intended reach of a connected care system. A circle on a map is not a verified patient catchment, a travel-time promise or a forecast of market share.
Use three planning layers: nearby communities for everyday and emergency care; a broader Valley network for scheduled specialty care and hospital transfers; and selected statewide referrals, teaching and research partnerships. Map actual road journeys, ambulance routes, weather, transport availability and payer access from each referring community. The earlier 1.5-hour corridor concept and its population assumption do not describe the entire expanded region; commission a new population and demand analysis.
Local clinics, teleconsultation, shared imaging, a staffed transfer center, patient shuttles and return-to-local-care agreements would connect the hospital to its region. Emergency routing must follow clinical need and the EMS system. A 100–200-mile referral ambition is not an instruction to bypass nearer emergency care or drive farther during a stroke.
The development stages: 150–200 → 350–450 → 600–700 beds
The earlier concept set out a roughly 200-acre district, a hospital ultimately reaching 600–700 beds, and 300–500 workforce homes. This edition restores that scale. The previous guide described a much smaller 100-bed / 100-home financial example as the full campus; that example is now clearly separated in the full campus guide.
Phase 0 — Master plan, feasibility and enabling work: establish operators, regional need, site control, financing and approvals. Reserve the land, circulation and infrastructure backbone for a 700-bed buildout from the beginning; engineers must decide what to install initially and what to add in modules. Early outpatient care, transport, housing and training can advance alongside hospital planning when independently viable.
The windows below come from the earlier concept and run from project initiation, not from publication of this article. They are planning horizons, not promised opening dates or mandatory waiting periods. Bring useful services forward when financing, approvals and staffing allow; reassess later phases against actual need. Each bed range is the cumulative campus total at that stage, not beds to add on top. Housing totals are also cumulative.
| Stage / planning window | Total hospital beds | Housing and services | Decision to advance |
|---|---|---|---|
| Phase I · Years 1–5 | 150–200 | Target about 300 workforce apartments / homes. First hospital, emergency department, general ICU, operating rooms, diagnostics, clinics, rehabilitation and training. Establish neurological assessment and transfer pathways; open advanced services only with the complete team. | A licensed, staffed and financed first hospital; housing operations funded; emergency and referral agreements in place. |
| Phase II · Years 5–12 | 350–450 | Expand toward the 300–500-home campus range as recruitment warrants. Expand inpatient and critical care. Prioritize a dedicated neuro ICU, neurointerventional stroke care and neurosurgery, alongside selected cardiac and cancer services. Grow education and rehabilitation. | Demonstrated referral demand, sustainable specialty volumes, 24/7 coverage, quality results, payer contracts and funding for each service. |
| Phase III · Years 12–25 | 600–700 | Complete the planning range of 300–500 workforce homes; reassess demand. Complete the regional referral hospital, deepen complex specialties, teaching and research, and pursue the trauma capability justified by the regional system. Retain future expansion space. | Measured regional benefit, staff recruitment beyond the existing local pool, an independently costed expansion and required service designations. |
A high-level neurological center directly in the Valley
Make advanced neurological care a central clinical program. The proposed center would connect emergency stroke assessment, catheter-based clot removal for eligible patients, neurosurgery, intensive neurological monitoring, and recovery. Its purpose is to shorten the path to the right team for patients who would otherwise face difficult transfers or repeated distant visits.
CDC identifies rapid stroke treatment as critical. UC Davis describes advanced stroke care combining emergency treatment, specialist monitoring and rehabilitation. Those sources support the clinical rationale; they do not establish how many Lyra patients would benefit or prove that a new site would improve their outcomes.
Plan the neurological program in Phase 0. Establish assessment, specialist consultation and transfer pathways with the first hospital. Target the dedicated advanced program during Phase II, with earlier opening possible if the full clinical team, case volume, facilities and approvals are ready. This makes neuroscience part of the core development plan rather than an undefined final-stage addition.
The service brief below is a proposed scope for clinical planning, not a certification checklist. A comprehensive stroke center and a Level I trauma center are distinct designations; neither follows automatically from bed count, a neuro ICU or the Stanford name. Specialist ICU and step-down beds must be allocated within the hospital total. Their exact number remains to be designed.
| Part of the neurological center | Proposed capability and support |
|---|---|
| Stroke and neurovascular intervention | Rapid brain and vessel imaging; stroke clinicians; a neurointerventional team and procedure suite for appropriate clot-removal and aneurysm procedures. Establish 24/7 readiness and transfer acceptance before advertising that capability. |
| Neurosurgery and neurocritical care | Brain and selected spine surgery; dedicated neuro ICU care, specialist nurses, neurointensivists, anesthesia, operating-room support, EEG monitoring, pharmacy and rehabilitation access. |
| Complex neurological care | Stage selected brain-tumor, epilepsy and other neurological services according to expertise, demand and outcomes. Neuro-oncology requires coordinated pathology, oncology and surgical care. |
| Recovery and continuing care | Physical, occupational and speech therapy; swallowing and cognitive assessment; caregiver education; follow-up near home; appropriate rehabilitation and step-down capacity. |
| Regional clinical network | Shared imaging and consultation, one transfer contact, transport agreements and return transfers when clinically appropriate. Partner hospitals retain essential local assessment and stabilization roles. |
Sources: [10] CDC · About stroke · [11] UC Davis Health · Stroke care · [12] UC Davis Health · Neurology services and specialties
A broader high-acuity mission
High acuity means caring for patients with serious, complex conditions who need intensive monitoring or specialist intervention. The regional hospital should be planned around teams, equipment and reliable service coverage as well as beds. The following are candidate programs to develop with operators; none is an announced service.
Build on California’s existing clinical network. UC Davis already describes comprehensive stroke care and specialist neurocritical and neurosurgical expertise. Map the actual capabilities, available capacity and referral patterns of Fresno, Modesto, Sacramento, Bay Area and other relevant hospitals before claiming an unmet service area. The question is where Lyra adds timely access and usable capacity.
| Program to evaluate | Potential regional contribution | Requirement before expansion |
|---|---|---|
| Advanced neuroscience | Treat selected stroke, brain injury and neurosurgical cases closer to their referring communities. | Complete specialist coverage, regional protocols, sufficient appropriate cases and tracked outcomes. |
| Critical care and complex surgery | Receive appropriate transfers, support major operations and reduce waits for a staffed intensive-care bed. | Critical-care teams, operating rooms, anesthesia, blood bank, diagnostics and funded step-down care. |
| Cardiac and vascular care | Develop selected catheter-based interventions and complex cardiovascular pathways. | Choose the exact program with operators; confirm surgical backup arrangements, staffing and demand. |
| Cancer care | Connect complex diagnostics, surgery, systemic treatment, radiation where justified, and clinical trials. | Specialty teams, equipment, pathology, research oversight and continuity with existing oncologists. |
| Trauma and other advanced services | Study a later trauma upgrade and additional services against the regional plan. | Separate designation and readiness process. Pediatric, neonatal and other distinct programs need their own staffing and demand case. |
Sources: [12] UC Davis Health · Neurology services and specialties
Apartments, family stays and a campus people can live with
Restore 300–500 workforce apartments / homes as the long-range planning range, with about 300 in the earlier Phase I concept. Include accessible homes and a mix for individuals and families, with rents, eligibility and operating support set out explicitly. Schedule housing early enough to support recruitment without assuming every unit must open before the first patient is admitted.
Patient and caregiver lodging is a separate program for a center drawing referrals from 100–200 miles away. Plan short stays, longer treatment stays, accessible rooms, meals, transport and navigation. Its unit count and funding are still to be determined; do not silently subtract it from the workforce-home target or count the same apartment twice.
Connect homes to childcare, training space, shaded walking routes, gardens, food access and dependable local transport. Prepare a separate housing and lodging business plan covering construction, maintenance, affordability and any explicit employer or charitable subsidy.
The master plan should reserve room for teaching and research, rehabilitation and family support, solar canopies and a resilient energy system. Engineer the microgrid, backup power, water and heat-resilience design against clinical requirements. Preserve I-5 and aqueduct geography; the existing concept image is not a survey or a verified site layout.
The positive impact: patients, families, the Valley and California
The central opportunity is access to definitive care closer to home, with the specialists and support needed to sustain it. Faster appropriate treatment could improve recovery; dependable local follow-up could reduce the burden of complex illness. These are expected pathways to benefit, not measured Lyra outcomes.
For California as a whole, a successful campus could add staffed referral capacity, distribute appropriate complex cases across more capable centers, expand training and clinical research, and provide additional options during regional surges. The statewide gain depends on creating capacity and growing the workforce, rather than simply moving scarce staff or existing patients from another Valley hospital.
Publish an annual regional-impact account comparing outcomes with the pre-opening baseline and comparable communities or care pathways. Report results by home county, payer, language and travel burden. Count unique patients separately from admissions, visits and transfers, and report both gains and any harm to surrounding providers.
| Who could benefit | Positive impact to test | How to establish the actual benefit |
|---|---|---|
| Patients needing neurological or other urgent specialty care | Earlier access to the appropriate specialist, procedure and staffed critical-care bed. | Referral-to-acceptance and treatment times; transfer refusals; risk-adjusted complications, mortality and functional recovery, including 90-day stroke outcomes. |
| Families and caregivers | Fewer long journeys, more time together during treatment and less disruption to work or caregiving. | Avoided round trips, travel hours, lodging and out-of-pocket costs, and patient/caregiver experience. |
| Valley hospitals and emergency services | Another reliable destination for cases beyond local capability, with a supported route back to local care. | Transfer waiting time and refusals; emergency-department boarding; ambulance turnaround; return-transfer performance; staffing effects on other hospitals. |
| California’s specialist-care network | Additional usable complex-care and surge capacity, with rare or highly specialized cases still directed to the right center. | Net new staffed beds and clinician hours across the network, eligible referrals completed, regional waits and outcomes. Count a shifted case only once. |
| The regional workforce | More local education, paid clinical placements, specialist recruitment and stable housing. | Graduates retained in the region, hard-to-fill shifts, turnover, vacancy rates, housing affordability and net workforce growth. |
| Patients eligible for research and advanced treatment | More opportunities for appropriate trials and coordinated specialty follow-up. | Trials offered, eligible participation, geographic and payer access, follow-up completion and patient-reported outcomes. |
What the larger capacity could mean
Explore the scale below using staffed beds, an assumed occupancy rate and an average length of stay. This estimates annual inpatient episodes at steady operation. It is not a demand forecast, a count of people newly helped, a staffing plan or a measure of lives saved. Specialist capacity depends on the actual bed mix and team availability.
A 650-bed example at 80% occupancy and a five-day average stay produces about 37,960 inpatient episodes per year. That is an arithmetic illustration of the larger vision. Visits, rehabilitation sessions and caregiver benefits should be measured separately; adding them does not produce a unique-patient total.
REGIONAL CAPACITY · ILLUSTRATIVE ARITHMETIC
Explore the hospital’s scale
At steady operation, under your assumptions. Admissions are not unique people, additional people served or lives saved. This does not forecast demand, outpatient care, neuro ICU capacity, revenue or treatment outcomes.
Why this part of the valley could make sense
The location concept is the Santa Nella–Los Banos–Gustine–Newman corridor around Highway 33, I-5 and Highway 152. It is a corridor hypothesis, not a selected parcel. Santa Nella offers a place to explore a western-valley hub; Los Banos and Gustine belong in the comparison, and Newman adds a neighboring-county connection.
The possible advantage is a campus that relates east–west travel to north–south travel while combining care and workforce housing. A large, phased site might accommodate growth more easily than a constrained urban location. Those are planning inferences: proximity to a freeway does not establish healthcare demand, low land cost, a usable interchange or access for people without cars.
Compare at least three locations on the same scorecard: a Santa Nella corridor parcel, an opportunity near established Los Banos services, and an option that improves access to existing regional facilities. Map 30-, 45-, 60- and 90-minute local catchments separately from the proposed 100–200-mile specialty-referral reach, by time of day; examine residents, actual Kaiser membership, referrals, payer mix, staffing and existing provider capacity. Include missed appointments, transit and caregiver journeys.
For each parcel, check zoning, agricultural restrictions, flood and drainage conditions, heat and air quality, water and wastewater capacity, electricity, emergency routes and the real cost of road access. Merced County’s zoning page links to parcel lookup by address or APN. A parcel map is the missing ingredient for a site-specific conclusion. [1, 2]
Different roles, one connected experience
Stanford role proposed for discussion: academic leadership and participation in advanced neurological care, selected complex inpatient specialties, diagnostics, procedures, teaching, research and referral pathways. Choose the service mix with clinical leaders and the regional demand study. This is a proposed substantial clinical presence, with exact responsibilities to be negotiated.
Kaiser role proposed for discussion: participation in hospital and specialty services alongside primary and urgent care, prevention, chronic-condition management, behavioral-health access, navigation and community programs. A Permanente medical group, the health plan and hospital entities would need to decide their own participation; “Kaiser” is not a single interchangeable contract.
Community access needs an explicit arrangement for Medi-Cal, Medicare, uninsured residents and people with other coverage. Include a local safety-net clinic or other willing providers where helpful. Co-location does not make every service covered by every plan, and a community program does not automatically give nonmembers access to Kaiser’s clinical network.
The earlier 50–50 capital/capacity concept is a negotiating starting point. Any shared specialty beds belong within the 600–700 total, not above it. No fixed split, governance model or contribution has been agreed by either institution.
A campus property arrangement could share land, utilities, parking, maintenance, selected equipment and training space. Clinical operators retain clearly assigned responsibility for care, staffing, records, licensing and quality. Agreements would set rents, reserved capacity, cost allocation, referrals, data access, liability and exit rights. Specialist counsel would test the ownership and contracting structure before commitments.
There is a relevant example of partnership beyond Kaiser’s own facilities: its August 2026 announcement described a $25 million grant and a loan of modular building capacity for MLK Community Hospital in Los Angeles. That supports exploring community partnerships and flexible construction; it does not establish interest in, or funding for, Lyra. [3]
What would actually be built?
The master plan reserves a district of roughly 200 acres for a 600–700-bed hospital, its clinical and support buildings, 300–500 workforce homes, patient/caregiver lodging, education and research, rehabilitation, childcare and future expansion. The acreage is a concept assumption, not a selected or controlled parcel. A clinical planner and architect must turn that program into a room schedule, bed mix and land-use plan.
Plan a campus framework first: accessible walking routes, shade, a shuttle/bus stop, utility corridors, safe emergency access, service areas and reserved expansion zones. Put shared support functions where they genuinely reduce duplication without creating bottlenecks. Separate public, clinical, residential and service circulation.
Use repeatable room layouts and structural grids, modular components where suitable, and mechanical/electrical capacity designed for specific future uses. A clinic should not be described as instantly convertible into an ICU: acuity changes can require different systems, structural standards, infection-control arrangements and approvals. The flexible design is a planned expansion strategy.
Housing and childcare should open early enough to support recruitment. A training partner could develop paid placements and career pathways with the care operators. Navigation, food support and family services need their own annual budgets and participating providers, even when they share space.
Keep the long-range ACE/rail and highway concepts in the vision, with a protected future connection if planners support it. Cost local campus access separately from a regional rail line or I-5/152 expansion. Those require separate sponsors, ridership or traffic analysis and capital/operating funding. Initial care should be reachable through existing roads and a practical bus/shuttle plan.
Fund each stage of the larger master plan
No defensible total construction price or operating forecast has yet been established for the 200-acre, 600–700-bed, 300–500-home master plan. Commission independent ranges for Phase I and each expansion, including neurological equipment and staffing, housing, family lodging, research space, infrastructure, escalation, financing and opening losses. Show each stage’s additional cost and the cumulative total.
The $500 million worksheet retained below models the earlier, smaller 100-bed / 100-home example. It does not price the restored Phase I, the neurological center or the ultimate campus. Its operating savings and travel benefits cannot be multiplied by bed count to claim the larger project’s return. The previous five-to-eight-year delivery scenario also belonged to that smaller program.
Use the master-plan stages for the development decision and the smaller worksheet only to understand funding mechanics. Keep clinical capital, workforce housing, patient lodging, education/research and regional transport in separate accounts. Assign an accountable operator and a funded annual budget to each. A rail line and highway works require their own sponsors and estimates.
The smaller financial example, retained for comparison
The earlier, smaller 100-bed / 100-home example totals $500 million. It is not a budget for any stage of the restored regional master plan. It compares that with $560 million for the same service program built separately. Potential gains are $60 million of avoided capital plus $14.7 million per year in shared operating savings. Another $9 million per year represents conditional payer and specialty-care gains. These are different benefits with different recipients, not one interchangeable funding pot.
The worksheet makes the argument inspectable. Change the budget, grant assumption, staffing efficiencies, operating cash or housing economics. The high-cost case and no-grant case show where the proposal would need to change. No probability is attached to a preset.
Open the smaller 100-bed / 100-home financial example
THE EARLIER, SMALLER COMPARISON
The 100-bed financial example
This worksheet retains the earlier 100-bed / 100-home example. It does not cost the regional master plan, its 150–200-bed first phase or the advanced neurological program. Amounts use September 2026 purchasing power without future escalation; they are invented assumptions, not local bids or operator forecasts.
The smaller example’s budget and sources
| Potential funding | Amount | Share of budget |
|---|---|---|
| Public grants — scenario target | $20M | 4% |
| Philanthropy / charitable gifts | $50M | 10% |
| Stanford / Kaiser or other operator cash | $180M | 36% |
| Private housing equity | $15M | 3% |
| Repayable bonds / loans | $235M | 47% |
| Total proposed sources | $500M | All uncommitted |
The illustrative sources balance with the budget. Identified commitments to this proposal: $0.
Private contributions total $245M. Borrowing is shown separately because it must be repaid. No county cash contribution or land donation is assumed. The no-grant preset exposes the gap without silently increasing borrowing.
See and change the construction budget
Default scope: roughly 60,000 sq ft community clinics, 60,000 sq ft specialty care, a 100-bed / 200,000 sq ft inpatient allowance, 100 homes and 20,000 sq ft of training/community space. These are the earlier example’s physical assumptions. Changing dollars or the housing rental count does not redesign or reprice the clinical program; this worksheet cannot validate the larger master plan.
What would two separate builds cost?
Hold the service scope, quality and patient volume constant. Start with $500M for the joint campus, then add the duplicated elements below: $560M in total. These additions must eventually be estimated from two actual designs.
Inputs stay in this page session. Download to keep your scenario. Model merced-campus-small-comparison-2026-09-21-v2.
Funding routes illustrated by the smaller example
Illustrative $500 million sources: $20 million public grants (4%); $50 million charitable gifts (10%); $180 million operator capital (36%); $15 million private housing equity (3%); and $235 million repayable debt (47%). That is $245 million of private cash/gifts/equity, $20 million in grants and $235 million borrowed. None is committed. County cash is assumed to be zero.
Organize a grant target by use before naming a program: for example, $15 million toward eligible community-care facilities, $2 million toward training infrastructure/programs and $3 million toward eligible community-access components. These are fundraising goals, not awards or verified eligible amounts. Program and timing checks can move the target to zero; recurring program grants must not be used to close a construction gap.
USDA Community Facilities is a screening conversation for an eligible rural public or nonprofit component. It requires qualifying rural geography, service-area income and financial need; grant shares are capped and funds limited. Large institutional resources may prevent eligibility. Do not apply the highest advertised percentage to the entire campus or create an artificial entity to evade the tests. Ask USDA to screen the actual applicant and project first. [4]
CHFFA revenue bonds could be explored by qualifying nonprofit healthcare borrowers. They are financing to repay, not a grant. Operator capital, foundations and philanthropy could cover equity-like support and specific community facilities; naming Stanford or Kaiser here does not assign a contribution. [5]
HCAI workforce programs may fit particular training activities, including primary-care training. They are not a general source for the whole hospital building. Affordable-housing tax credits could attract private equity only for a qualifying restricted rental component, with compliance obligations; do not count that equity twice or assume all workforce homes qualify. [6, 7]
California’s Infill Infrastructure Grant page was closed to applications when checked. Its affordable-housing and infill focus also makes a greenfield campus an uncertain fit. Keep it on a watchlist, with $0 assigned to it in underwriting. The model’s public-grant target is deliberately unallocated until real eligibility is established. [8]
Assign the example’s housing its own $36 million account: $15 million private equity plus $21 million debt. The remaining $464 million clinical/community campus uses grants, gifts, operator capital and $214 million debt. A housing subsidy, public land discount or utility contribution must be shown explicitly if one is proposed later.
Why the combined investment could be more useful
The financial case has three comparisons. First, one shared campus versus two facilities providing the same service: that is where duplicated capital and operating costs can fall. Second, the campus versus continuing or improving existing care: that asks whether any new campus is justified. Third, the household and community consequences: access, time, housing, training and stability.
In the smaller example only, allocating shared operating savings equally gives Stanford $7.35 million and Kaiser $7.35 million per year. Add $5 million of assumed net new specialty contribution for Stanford and $4 million of retained payer savings for Kaiser: $12.35 million and $11.35 million respectively. These are conditional mature-year gains, not institutional forecasts or net investment returns.
The strongest version of the idea is that the pieces reinforce each other: housing and childcare help staffing; training supports recruitment; local care reduces difficult journeys; coordinated pathways keep specialist time focused on appropriate cases. Verify those links before counting them twice. A reduction in hospital revenue is not automatically a loss for the overall care system, but the payment agreement must make the providers sustainable.
At the default travel assumptions, 40,000 avoided distant round trips save households $1.08 million of vehicle expense and return 80,000 person-hours, valued illustratively at $2 million. Those benefits matter to residents; they do not pay a hospital’s debt service. Improved health and family stability are left as outcomes to measure rather than speculative dollar totals.
The default housing account does not fully cover its own debt at the assumed rent and occupancy. That is a useful design question: reduce cost or debt, obtain more housing equity, or budget an explicit employer subsidy. The combined clinical example clears its chosen mature debt-coverage test, but early operating losses and uncommitted capital still need a real plan.
A practical first 90 days with Merced County
Days 1–15 — Prepare a county discussion packet: the full vision, assumed service scope, a diagram of phased campus uses, two or three candidate parcels/APNs, a preliminary access concept, the model and an open-questions list. Name a project coordinator. Seek preliminary interest from potential clinical, housing and education partners; do not describe invitations as commitments.
Days 15–30 — Request a coordinated pre-application meeting with Merced County Planning / Community & Economic Development. Planning lists (209) 385-7654; CED lists (209) 385-7686. Ask which department should convene planning, building, public health/EMS, public works, fire and environmental health, and which external utilities and agencies should attend. No meeting has been requested on this proposal’s behalf. [1]
Leave that meeting with a written route for each parcel: existing designation and allowed uses; possible plan/zoning changes and discretionary permits; environmental review; agricultural or other restrictions; required traffic, drainage and utility studies; review fees; decision-making bodies; and who owns each next action. Ask staff which issues can be resolved in parallel. The county determines the applicable process.
Days 30–60 — Obtain preliminary utility capacity and connection-cost responses, a clinical building-scope consultation and a demand/catchment study brief. Ask prospective operators to test member demand, payer contracts, specialties, transfers and staffing. Request nonbinding partner statements that identify the work they might explore rather than imply a deal.
Days 45–75 — Commission a concept plan and independent cost range for the complete campus and each phase. Take the actual applicant and uses to USDA and other prospective funders for eligibility screening. Ask potential lenders what recurring cash and security they would require. Prepare a funding tracker: amount, use, recipient, match, timing, restrictions and evidence.
Days 60–90 — Publish the options and tradeoffs for local discussion. Compare the parcels, a shared campus, and improvements to existing services. Choose whether to fund formal feasibility and site control, narrow the scope or stop. If advancing, negotiate a time-limited, conditional option instead of assuming a land purchase is the first step.
From a concept plan to permission to open
County land-use and environmental review, utility approvals, healthcare building review, clinical licensing and payer agreements are separate workstreams. Ask HCAI to determine the building-review scope for each clinical component; its construction resources describe the review and permit process. Ask the relevant licensing authority to define the route for each proposed service. County planning approval alone does not authorize patient care. [9]
Ask the county to identify the road owner for every access improvement and whether state highway access requires Caltrans involvement. Verify service boundaries and whether a special district or LAFCO process is implicated before assuming utility extensions. A possible rail connection needs its own operator and infrastructure agreements.
Before construction: settle the operator agreements, design scope, approvals, infrastructure obligations, financing commitments, contingency, opening reserve and schedule. Before opening: verify staffing, service licenses, payer arrangements, emergency/transfer plans, equipment commissioning and a funded operating budget. Each phase needs to function safely on its own.
Help make the possibility more concrete
For residents: which journey, missing service or family support would make the largest difference? For clinicians: which shared facilities would help, and which should remain separate? For employers and educators: what would make a local training-and-housing arrangement useful?
For neurological and other high-acuity teams: where would a new center most improve timely treatment, how should it work with existing hospitals, and what staffing would make it sustainable?
For funders and county staff: which component has a credible route to eligibility, approvals and ongoing support? For everyone: what is the strongest alternative, and what evidence would favor this campus? Add your perspective below. The aim is to improve an idea that could benefit the region.
What changed in this edition
September 21, 2026 · Restored the earlier 200-acre, 600–700-bed and 300–500-home concept with cumulative development stages. Added the proposed 100–200-mile referral reach, a dedicated neurological program and a regional/statewide impact framework. The $500 million, 100-bed / 100-home example is retained as a smaller comparison. All capacities, dates and partner roles remain planning assumptions.
Sources & reading
- [1] Merced County · Planning and department contactsOfficial planning contacts and review resources. Checked September 11, 2026; not a project determination.
- [2] Merced County · Zoning and parcel lookupParcel lookup is needed before assigning zoning or buildability to a location.
- [3] Kaiser Permanente · MLK Community Hospital partnershipAugust 11, 2026 announcement. A different project, cited only as a community partnership/modular-building example.
- [4] USDA · Community Facilities Direct Loan & GrantApplicant, rural geography, income, financial-need and eligible-cost tests apply. No Lyra eligibility established.
- [5] CHFFA · Bond financingPotential financing pathway for eligible nonprofit borrowers; repayable debt.
- [6] HCAI · Workforce grantsProgram-specific workforce support; verify current windows, eligible uses and applicants.
- [7] California Tax Credit Allocation CommitteeAffordable rental housing tax-credit program and compliance resources. No allocation assumed.
- [8] HCD · Infill Infrastructure GrantClosed when checked September 11, 2026; infill/affordable-housing fit unresolved. Assigned $0 to this specific program.
- [9] HCAI · Building and construction projectsOfficial healthcare construction process resources; facility-specific scope determination required. Reviewed September 21, 2026.
- [10] CDC · About strokeRapid treatment and stroke-related disability. Reviewed September 21, 2026; not a Lyra outcome estimate.
- [11] UC Davis Health · Stroke careExisting model of emergency treatment, monitoring and rehabilitation. Reviewed September 21, 2026; no partnership implied.
- [12] UC Davis Health · Neurology services and specialtiesExisting comprehensive stroke, neuro-oncology, brain-injury and specialist care. Reviewed September 21, 2026; not evidence of local unmet demand.
Concept development: Kevin G. Founding text prepared with AI assistance for editorial review. These proposals explore possibilities; they do not announce approved projects.
Published revision history
Version 2 · 2026-09-21
Preserved before the regional master-plan restoration
Version 2 · 2026-09-21
Restored at the owner’s request: regional reach, cumulative hospital and housing phases, advanced neurological care, high-acuity impact and corrected financial-example scope.
Version 1 · 2026-09-11
Full-campus possibility guide with editable assumptions, funding and county implementation steps
HELP SHAPE THE NEXT IDEA
What should we explore next?
Send an idea, a thoughtful challenge, a correction or experience from your community. Tell us what could improve, who it would help and what it would take.
How to contribute →
THE CONVERSATION
What would make this idea better?
Share a question, a local perspective, or a way to improve the proposal. Thoughtful disagreement is welcome.
Loading comments…