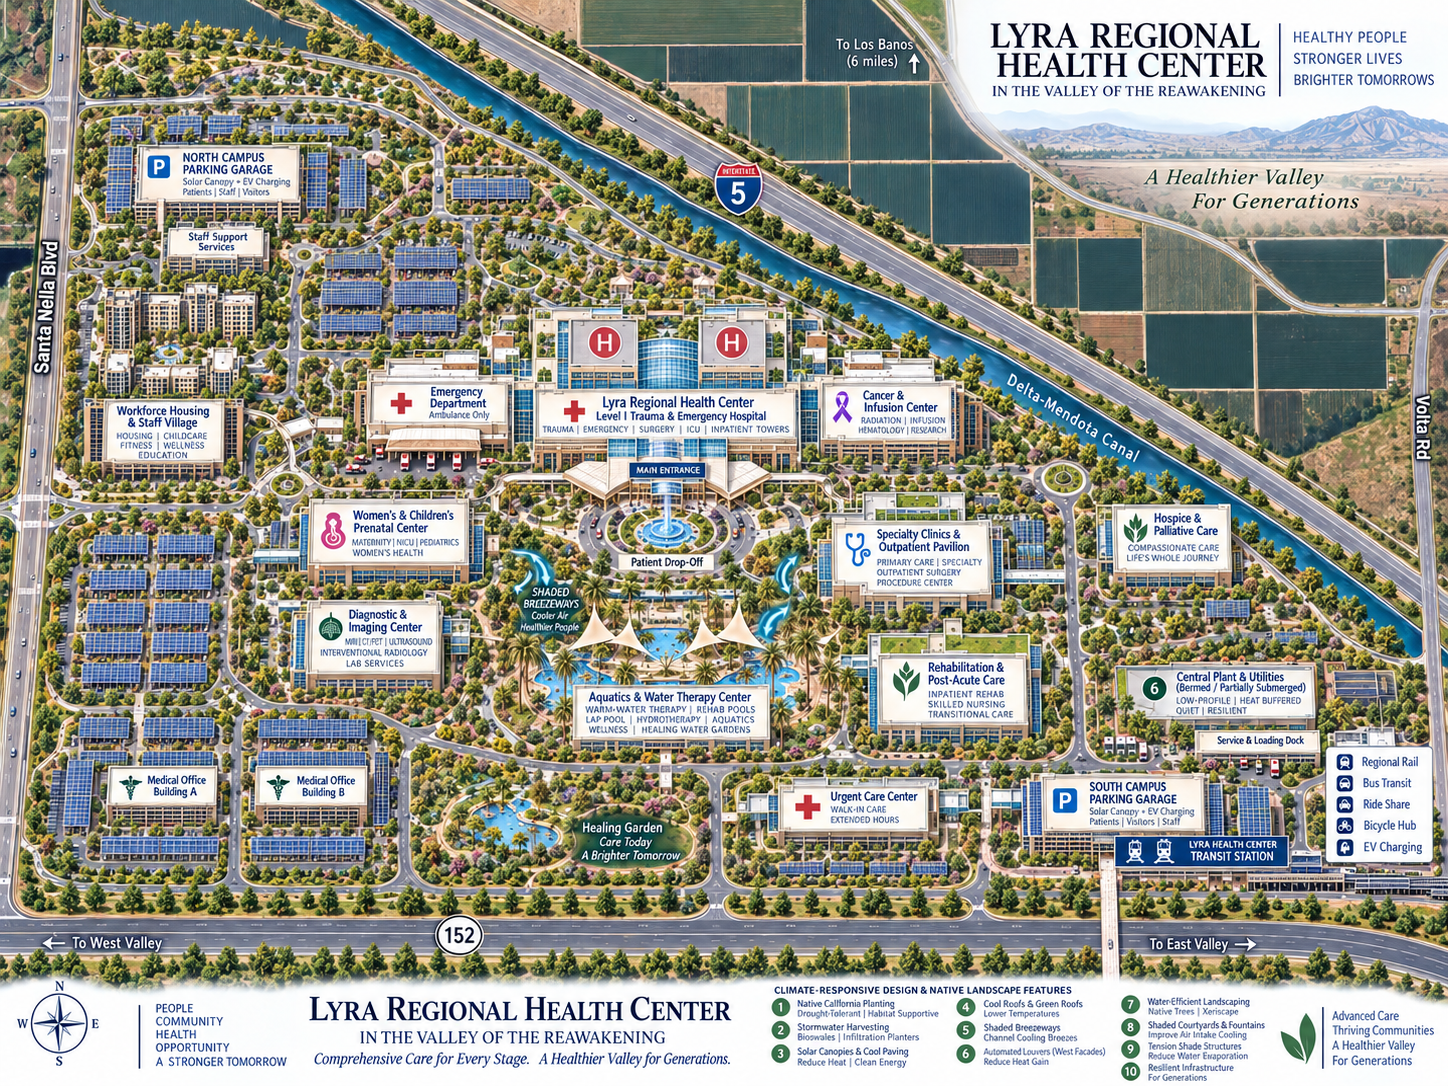
EXPLORE THE FULL IDEA
One campus. Many possible gains.
Explore the 100–200-mile regional vision: three hospital phases, 600–700 eventual beds, advanced neurological care, 300–500 workforce homes and the potential impact across the Valley and California.
Read the full campus guide →The problem to establish
Can people in the western valley reach appropriate care reliably, and could a regional service reduce the burden? This is the starting question, not an established finding of unmet demand. A local baseline needs travel times, referral patterns, service availability and residents’ experiences.
No operating partner, site, bed count or construction budget is confirmed.
The shared goal
More dependable access to appropriate care, with a service that patients can reach and clinicians can staff. Judge success by access, quality and operating stability.
The regional vision
Plan a roughly 200-acre Stanford–Kaiser health district near Santa Nella, ultimately reaching 600–700 beds and 300–500 workforce homes. A specialty-referral network would aim to serve communities roughly 100–200 miles around the hospital, with local care, transport, family lodging, education and research connected to it. These are conceptual targets; no institutional participation or site is confirmed.
Make advanced neurological care a central program: stroke intervention, neurosurgery, neurocritical care and rehabilitation. Develop other high-acuity specialties around demonstrated need, trained teams and sustainable operations. Clinical bed allocations are part of the overall hospital total.
The development stages: 150–200 → 350–450 → 600–700 beds
The earlier concept set out a roughly 200-acre district, a hospital ultimately reaching 600–700 beds, and 300–500 workforce homes. This edition restores that scale. The previous guide described a much smaller 100-bed / 100-home financial example as the full campus; that example is now clearly separated in the full campus guide.
Phase 0 — Master plan, feasibility and enabling work: establish operators, regional need, site control, financing and approvals. Reserve the land, circulation and infrastructure backbone for a 700-bed buildout from the beginning; engineers must decide what to install initially and what to add in modules. Early outpatient care, transport, housing and training can advance alongside hospital planning when independently viable.
The windows below come from the earlier concept and run from project initiation, not from publication of this article. They are planning horizons, not promised opening dates or mandatory waiting periods. Bring useful services forward when financing, approvals and staffing allow; reassess later phases against actual need. Each bed range is the cumulative campus total at that stage, not beds to add on top. Housing totals are also cumulative.
| Stage / planning window | Total hospital beds | Housing and services | Decision to advance |
|---|---|---|---|
| Phase I · Years 1–5 | 150–200 | Target about 300 workforce apartments / homes. First hospital, emergency department, general ICU, operating rooms, diagnostics, clinics, rehabilitation and training. Establish neurological assessment and transfer pathways; open advanced services only with the complete team. | A licensed, staffed and financed first hospital; housing operations funded; emergency and referral agreements in place. |
| Phase II · Years 5–12 | 350–450 | Expand toward the 300–500-home campus range as recruitment warrants. Expand inpatient and critical care. Prioritize a dedicated neuro ICU, neurointerventional stroke care and neurosurgery, alongside selected cardiac and cancer services. Grow education and rehabilitation. | Demonstrated referral demand, sustainable specialty volumes, 24/7 coverage, quality results, payer contracts and funding for each service. |
| Phase III · Years 12–25 | 600–700 | Complete the planning range of 300–500 workforce homes; reassess demand. Complete the regional referral hospital, deepen complex specialties, teaching and research, and pursue the trauma capability justified by the regional system. Retain future expansion space. | Measured regional benefit, staff recruitment beyond the existing local pool, an independently costed expansion and required service designations. |
Why the larger vision matters
The potential gains include more timely specialist treatment, fewer difficult transfers, reduced family travel, additional staffed referral capacity and a stronger regional training pipeline. Test the net benefit to California against current care pathways, patient outcomes and staffing effects on surrounding hospitals. The full campus guide sets out the neurological program and the impact measures.
The $500 million example in the guide covers an earlier 100-bed / 100-home program. It does not price the restored master plan or establish its total positive impact.
The alternatives deserve a fair test
Baseline: improve access to existing providers. Modest options: visiting specialists, transport support, a clinic or limited outpatient care. Larger option: a regional facility justified one phase at a time.
Use the same population, quality measures, time horizon and cost definitions for every option. A smaller service may answer the need better.
Who pays—and who benefits?
Capital includes land, site preparation, utilities, construction, equipment and financing. Operations include staffing, insurance, maintenance, supplies, administration and reimbursement. Separate housing costs from clinical operations.
Patients and caregivers may gain time; workers may gain employment access. Nearby residents could face traffic, disruption or land-use changes. Investigate these outcomes with affected people.
Evidence and uncertainty
No completed feasibility study supports this concept. Collect provider capacity and utilization data, operator interviews, staffing requirements and patient travel evidence. Ask an independent reviewer to challenge demand estimates.
Reimbursement, recruitment, water, utilities and housing affordability could each change the proposal.
Models and assumptions
The worksheet below demonstrates arithmetic. Its inputs are illustrative, not local estimates. Document capital, annual operations and annual revenue separately. Financing, inflation and lifecycle replacement are not included.
Original operating-gap illustration
ILLUSTRATIVE SCENARIO · USD
Change the assumptions.
Try the arithmetic. Starting values are deliberately illustrative and carry no local feasibility claim.
Formula: annual cost − annual revenue. Excludes capital financing, inflation and lifecycle replacement. Inputs are not saved.
Policy and funding
SB 79 is a related housing-policy example. Its direct application to a Santa Nella location is unresolved. No grant award, project authorization or appropriation is established.
Who needs to be at the table?
Patients, caregivers, clinicians and prospective operators; local planning and utility authorities; education providers; independent finance and health-services reviewers. Directory listings are research starting points, not committed partners.
The next decision
Identify a credible prospective operator and prepare a bounded needs-and-options brief. Decide whether a defined service gap merits formal feasibility work before selecting a facility.
Record history
September 21, 2026 · Restored the regional scale and three hospital-development phases from the earlier concept; added neurological care and broader impact. September 11, 2026 · Founding concept. No feasibility, financing or implementation approval is implied.
Sources & reading
- California Legislative Information · SB 79 chaptered text2025–2026 session. Historical chaptered text checked September 11, 2026. Later law changes require separate review.
- MCAG · Official regional planning and agenda resourcesOrganizational resources checked September 11, 2026. No commitment to these proposals is established.
- California HCAI · Data and facility resourcesResearch starting point; no local demand estimate has been produced.
Concept development: Kevin G. Founding text prepared with AI assistance for editorial review. These proposals explore possibilities; they do not announce approved projects.
Published revision history
Version 2 · 2026-09-21
Preserved before the regional master-plan restoration
Version 2 · 2026-09-21
Restored at the owner’s request: regional reach, cumulative hospital and housing phases, advanced neurological care, high-acuity impact and corrected financial-example scope.
Version 1 · 2026-09-11
Initial concept brief; editor approval pending public launch
HELP SHAPE THE NEXT IDEA
What should we explore next?
Send an idea, a thoughtful challenge, a correction or experience from your community. Tell us what could improve, who it would help and what it would take.
How to contribute →
THE CONVERSATION
What would make this idea better?
Share a question, a local perspective, or a way to improve the proposal. Thoughtful disagreement is welcome.
Loading comments…